
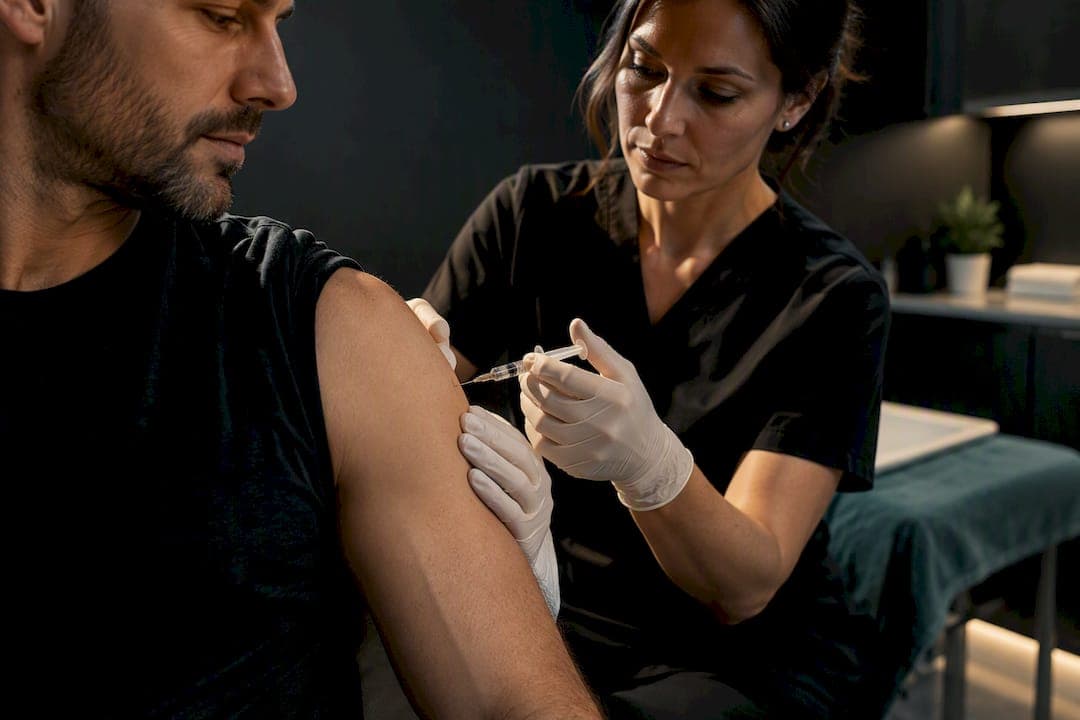
Vitamin D injections help people who cannot absorb or reliably take oral supplements. For most others, oral vitamin D works just as well when taken correctly. The benefit comes from restoring your blood level of 25-OH vitamin D, not from the injection itself, and that level needs monitoring whichever route you choose.
TL;DR:
- Vitamin D injections are mainly suitable for severe deficiency, malabsorption, or documented non-adherence to oral supplements, not as a routine alternative.
- Injections deliver a gradual release of vitamin D from muscle tissue, with blood levels rising within days and plateauing over several weeks.
- Most people should start with oral vitamin D, which is effective when taken consistently, reserving injections for cases where oral therapy is ineffective or impractical.
- Injections are typically administered as a single high-dose bolus, with follow-up testing at 6 to 12 weeks to verify optimal vitamin D levels.
- Cost and insurance coverage generally favor oral supplementation, making injections a more expensive option reserved for specific clinical indications.
Table of Contents
- Health benefits of vitamin D and why serum levels matter
- How injections compare with oral vitamin D
- Clinical indications: who should consider an injection
- Regimens, onset and duration: what to expect after an injection
- Safety, side effects and monitoring you must know
- How Rivers Edge Skin Studio approaches vitamin D injections
- Short summary and immediate next steps
- Cost considerations and insurance coverage for vitamin D injections
- Efficacy evidence from clinical trials supporting vitamin D injections
- Recommendations or guidelines from health authorities regarding vitamin D injections
- Potential side effects and contraindications specific to vitamin D injections
- Comparison of vitamin D injection benefits relative to other supplementation methods
- What this looks like in practice
- Book a supervised vitamin D injection
- Authoritative guidance and representative studies
- Sources
- FAQ
Health benefits of vitamin D and why serum levels matter
Vitamin D supports three systems that men notice when they are running low: bone mineralisation, muscle function, and immune regulation. Deficiency shows up as tiredness, aching bones, and slower recovery from minor illness.
None of these benefits come from the vitamin sitting in your bloodstream. They come from your serum 25-OH vitamin D reaching and staying at a level your body can use.
- Bone health depends on vitamin D helping you absorb calcium properly.
- Muscle function relies on adequate vitamin D to support strength and reduce fall risk in older men.
- Immune regulation is one of the roles vitamin D plays, though research does not support it as a general infection-prevention tool.
A single small trial found that a vitamin D injection improved insulin sensitivity and beta-cell function in vitamin D–deficient men after exercise, but it did not show broader anti-inflammatory or muscle-repair advantages beyond what restoring vitamin D status would explain. That distinction matters when you see wellness clinics promising more than the evidence shows.
How injections compare with oral vitamin D
The pharmacokinetics differ sharply. An injection delivers a large dose into muscle tissue, which then releases slowly, creating a gradual rise rather than an immediate spike. Oral vitamin D depends on gut absorption, taken daily, weekly, or as a periodic loading dose.
UK formulary guidance recommends oral vitamin D as first line, noting that intramuscular administration has unpredictable bioavailability and is generally kept as a second-line option. A separate randomised trial comparing the two routes found both replete vitamin D effectively, though the injection group had a higher mean level at 12 weeks in that particular study.
What tips the decision one way or the other:
- Malabsorption conditions or swallowing difficulty make injections the more reliable route.
- A pattern of missed doses or inconsistent adherence to oral tablets favours a supervised injection instead.
- Controlled, gradual dosing and lower toxicity risk favour oral therapy for most healthy adults.
Neither route is inherently superior. The right one depends on whether your gut can absorb what you swallow and whether you will actually take it consistently.
Clinical indications: who should consider an injection
Injections are considered for specific situations, not as a general upgrade on oral supplements.
- Severe, laboratory-confirmed deficiency where oral repletion has failed or would take too long.
- Malabsorption conditions, such as inflammatory bowel disease or prior bariatric surgery, that limit gut uptake.
- Documented non-adherence to oral regimens, where a clinician has tried oral dosing without success.
- Certain inpatient or clinical settings where oral dosing is impractical.
Before any injection, testing baseline 25-OH vitamin D and calcium is standard practice, and a result outside expected ranges should trigger specialist referral rather than repeat dosing. For most people without these specific issues, an oral regimen remains the appropriate and effective starting point.
Regimens, onset and duration: what to expect after an injection
A common intramuscular loading scheme uses a single high-dose bolus, with an equivalent oral alternative spread over several weeks. The BNF lists regimens such as 300,000 units given intramuscularly for patients who cannot tolerate oral preparations, alongside oral loading schedules for those who can.
- Serum levels begin rising within days but take several weeks to plateau.
- Symptomatic improvement, when deficiency was the cause of symptoms, tends to follow the serum rise rather than precede it.
- Follow-up testing at 6 to 12 weeks confirms whether the dose achieved its target.
A trial comparing oral weekly dosing against a single injection found both routes replete vitamin D over 12 weeks, with the injection group showing a higher average level at that point. Maintenance therapy after either route usually shifts to a lower, ongoing oral dose.
Safety, side effects and monitoring you must know
Vitamin D toxicity is rare but serious. It develops when repeated high doses push calcium absorption too high, leading to hypercalcaemia, which can cause nausea, confusion, and in severe cases kidney strain.
- Local injection-site soreness or a small lump is the most common reaction.
- Systemic issues are uncommon at guideline-recommended doses but become more likely with repeated boluses given too close together.
- Baseline testing of 25-OH vitamin D and calcium is standard before dosing, with repeat testing before any second bolus.
Pro Tip: Never accept a repeat vitamin D injection without a recent blood test confirming your level actually needs it.
How Rivers Edge Skin Studio approaches vitamin D injections
Rivers Edge Skin Studio treats vitamin D injections as a supervised clinical service, not a walk-in wellness add-on. The process runs from consultation through baseline bloods to a tailored dose and a follow-up review, matching the monitoring principles set out in UK formulary guidance. Men who have already discussed oral options with a GP and still need a supervised injection can find that pathway here, delivered within a men's clinic environment.
Short summary and immediate next steps
Injections suit people with confirmed malabsorption, severe deficiency, or a real pattern of missed oral doses. Most men are better served by oral vitamin D taken consistently. Start with a blood test, discuss the result with a clinician, and treat a supervised injection as the option for a specific, confirmed need rather than a first choice.
Cost considerations and insurance coverage for vitamin D injections
Cost varies depending on where you have the injection done and whether it is provided through routine NHS care or privately. NHS provision typically follows formulary guidance, meaning injections are reserved for the clinical indications already covered, such as confirmed malabsorption or documented non-adherence, and are usually only funded when oral options have genuinely failed. Private clinics charge per session, and pricing differs by provider and by whether blood testing is bundled in.
At Rivers Edge Skin Studio, a Vitamin D Injection is priced at £45 as a one-off treatment. This reflects a single administered dose rather than a course, and testing or consultation may be arranged separately depending on your situation.
Insurance coverage for vitamin D injections specifically is inconsistent. Private medical insurance policies in the UK generally do not cover routine vitamin supplementation, including injections, unless a specialist has identified a specific medical condition requiring it as part of a wider treatment plan. If you are relying on insurance, check your policy wording rather than assuming wellness-adjacent treatments are included.
The practical takeaway is that cost should not be the deciding factor between oral and injectable vitamin D. Oral supplementation is inexpensive and, for most people, equally effective when taken consistently. An injection becomes worth paying for when your situation matches one of the clinical indications already outlined, not simply because it feels like a faster or more premium option.
Efficacy evidence from clinical trials supporting vitamin D injections
The clinical trial evidence for injectable vitamin D is narrower than wellness marketing suggests, but it is real. A randomised study comparing oral weekly cholecalciferol against a single intramuscular bolus found that both routes successfully repleted vitamin D, with the injection group reaching a higher mean serum level at 12 weeks in that particular cohort.
A separate open-label randomised trial testing daily, weekly, and monthly dosing schedules reported that the monthly intramuscular group achieved higher sufficiency rates at 12 weeks than the equivalent oral regimens tested in that study. This kind of result supports injections as a legitimate option where adherence to daily or weekly oral dosing is the barrier, rather than evidence that injections outperform oral vitamin D in every circumstance.
A smaller trial in vitamin D deficient men found that a single injection improved insulin sensitivity and beta-cell function measured after exercise, compared with controls. Importantly, the same trial did not find broader anti-inflammatory or muscle-damage benefits beyond what restoring vitamin D status would explain, which is a useful check against inflated claims about injections delivering effects unrelated to correcting the deficiency itself.
Taken together, the trial evidence supports intramuscular vitamin D as effective for repletion, particularly in cohorts prone to inconsistent oral adherence. It does not establish injections as generally superior for wellness, energy, or immune outcomes beyond what correcting a genuine deficiency would achieve through either route.

Recommendations or guidelines from health authorities regarding vitamin D injections
UK clinical guidance is consistent on one point: oral vitamin D is the first-line treatment, and injections are a second-line option. NICE's clinical knowledge summary on vitamin D deficiency in adults sets out testing thresholds and targeted repletion strategies, alongside prevention advice of 10 micrograms daily for adults at risk of deficiency.
The BNF's ergocalciferol monograph lists intramuscular dosing regimens, including single doses around 300,000 units, specifically for patients who cannot tolerate or absorb oral preparations. It also flags variability in absorption as a reason injections are not the default choice.
Local NHS trust formularies echo this position. Guidance reviewed for this article states that injections may be used for deficiency when oral dosing is not possible, but should be monitored closely due to variability in absorption and the risk of toxicity from cumulative dosing. The consistent thread across these sources is that intramuscular vitamin D is a tool for specific clinical scenarios, used under medical supervision with blood monitoring, not a routine upgrade over tablets.
This matters because wellness clinics sometimes frame injections as inherently more powerful. The guidance does not support that framing. It supports injections as the right tool for malabsorption, severe deficiency, or genuine non-adherence, delivered with the same testing discipline as any other prescribed treatment.
Potential side effects and contraindications specific to vitamin D injections
The most common side effect is local: soreness, mild swelling, or a small lump at the injection site, which usually resolves within days. Systemic side effects are uncommon when dosing follows guideline recommendations, but they become more likely when repeat boluses are given too close together without checking levels first.
Vitamin D toxicity is the serious risk to understand. It develops from excess calcium absorption driven by high vitamin D levels, and it can cause nausea, vomiting, confusion, and in severe cases kidney problems. This is why baseline calcium testing sits alongside vitamin D testing before any injection.
Contraindications include known hypercalcaemia, certain kidney conditions where calcium regulation is already impaired, and conditions such as sarcoidosis where vitamin D metabolism is altered. Anyone with these conditions needs specialist input rather than a routine injection.
The same caution that applies to loading doses in supervised clinical settings applies here: a repeat bolus should never be given without a recent blood test confirming it is actually needed, exactly as covered under monitoring above.
Comparison of vitamin D injection benefits relative to other supplementation methods
Set side by side, the three main routes, injection, daily oral dosing, and periodic high-dose oral loading, differ mainly in speed of absorption and how much they depend on you remembering to take something.

Injections bypass the gut entirely, which makes them the most reliable route when malabsorption is the problem. The trade-off is a less controllable release pattern, since the dose sits in muscle tissue and disperses gradually rather than being fine-tuned day to day.
Daily oral dosing is slower to build up but easiest to adjust, and it carries the lowest toxicity risk because doses are small and spaced out. Periodic high-dose oral loading sits in between: faster than daily dosing, still gut-dependent, and useful for people who struggle with daily pill-taking but can manage an occasional larger dose.
For raw speed for someone who cannot absorb oral doses at all, injection is the more dependable choice. For someone whose gut works fine but who simply forgets tablets, a weekly or monthly oral schedule solves the adherence problem without the unpredictability of intramuscular release. Neither route beats the other in general terms. Each solves a different failure point, gut absorption versus daily consistency, and the right choice depends on which failure point actually applies to you.
What this looks like in practice
Testing before treating is the principle I keep coming back to. Men often assume tiredness means low vitamin D and reach straight for an injection, when a blood test just as often shows a normal level and a different cause behind the fatigue.
The pattern worth remembering is that restoring a genuinely low level, whichever route gets you there, is what produces the improvement. Placeholder credentials aside, that is the standard this article has tried to hold to throughout.
— David
Book a supervised vitamin D injection
If your GP has confirmed you need a vitamin D injection rather than oral tablets, Rivers Edge Skin Studio offers a supervised pathway built around testing first, not guesswork.
- Consultation to review your history and any existing blood results.
- Baseline testing arranged where needed before any dose is given.
- A tailored injection followed by a scheduled follow-up review.
Booking is handled through our services page, where the Vitamin D Injection sits alongside our other wellness and skin treatments for men. If you are still deciding between oral and injectable options, our piece on vitamin B12 injection benefits covers the same supervised approach for a related injectable.
Authoritative guidance and representative studies
This article draws on NICE clinical guidance, BNF drug monographs, NHS trust formularies, and peer-reviewed trials comparing oral and intramuscular dosing.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- PubMed: study (31701851)
- Shropshire and Telford formulary guidance (2025)
- PMC article: oral versus IM cholecalciferol (2016)
- NICE clinical knowledge summary: vitamin D deficiency in adults
- BNF: ergocalciferol drug monograph
FAQ
How quickly does a vitamin D injection take to work?
Serum vitamin D levels begin rising within days of an injection, but the full effect builds over several weeks as the dose disperses from muscle tissue. Symptomatic improvement, where deficiency was the cause, typically follows the serum rise rather than happening immediately.
How long will a vitamin D injection last?
A single loading dose is generally intended to correct a deficiency over roughly 12 weeks, after which follow-up testing determines whether levels have stabilised. Ongoing maintenance after that point usually shifts to a lower-dose oral regimen rather than repeated injections.
Is it worth getting a vitamin D injection?
It is worth it if you have confirmed malabsorption, severe documented deficiency, or a genuine pattern of missing oral doses, since UK formulary guidance reserves injections for these situations. For most people without these issues, oral vitamin D taken consistently is equally effective and considerably cheaper.
What happens after a vitamin D injection?
You may notice mild soreness at the injection site for a day or two, which usually resolves on its own. Your clinician will typically schedule a follow-up blood test at 6 to 12 weeks to confirm your vitamin D and calcium levels have responded as expected.